Safety Awareness Deep Dive Part 1 of 4
Safety Awareness in EVS, Part 1 of 4: The Needle You Never Saw Coming I went deep into safety research…
Safety Awareness in EVS, Part 1 of 4: The Needle You Never Saw Coming I went deep into safety research…
King County Washington. In January 2024, Washington State confirmed its first locally acquired cases of Candida auris there, traced to…
OSHA’s Safe & Sound Week ran August 10 to 16. It’s a voluntary campaign built on three things: management leadership, worker participation, and finding and fixing hazards before they find you. Participation is voluntary. The hazards it’s about are not.
Every EVS department has a version of the same list, and most of it has gone quiet. Overfilled trash and linen bags. Sharps disposed of improperly by clinical staff, not EVS. Cart wheels that have been bad for months. Chemical splash risk. Wet floors. Repetitive lifting. Workplace violence. None of these are secrets. They’re conditions a team sees so often that seeing them stops counting as noticing them.
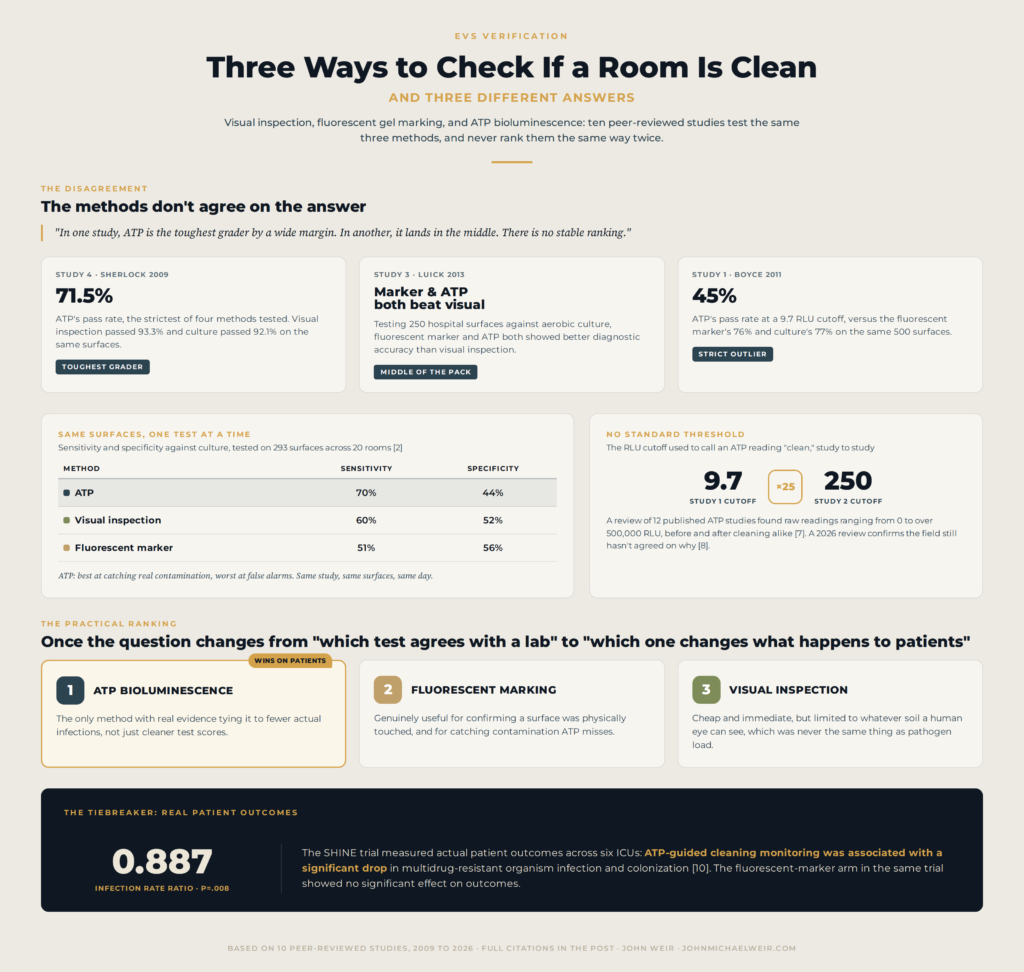
Two days ago I wrote about three ways to check if a room is clean: visual inspection, fluorescent marker, and ATP testing. All three exist because none of them fully agree with each other, and none of them is the one your patient is actually using.
A patient forms an opinion about your hospital before anyone tells them the room passed any of those three tests. They form it by looking around: no dust on the windowsill, no wrapper in the trash, how the floor looks, a bed made square. That opinion becomes data. It shows up on a federal survey, and that is how the next patient hears about your hospital before they walk through the door.
Clostridioides difficile forms a spore that survives almost everything you’re using to disinfect a room. Standard hospital-grade disinfectant, the quaternary ammonium product most departments use every day, was never designed to kill it. Spores don’t have the metabolic machinery those chemistries attack. You can wipe a rail until it shines and the spore is still there, waiting for the next patient’s hands.
Sodium hypochlorite (Clorox Healthcare Bleach Germicidal Wipes) and peracetic acid-based products make up the overwhelming majority of EPA List K, the actual registered list of products with a kill claim against C. diff spores. Here’s the detail some training materials get wrong: the accelerated hydrogen peroxide products a lot of departments already stock for daily disinfection, the Oxivir and Accel lines, do carry a genuine C. diff sporicidal claim in Canada under Health Canada registration. They do not carry that claim here. If your daily disinfectant isn’t actually on EPA List K in the United States, it isn’t touching the spore, no matter how hospital-grade the label says it is.
Ask an Environmental Services (EVS) program how it knows a room is clean, and you’ll get one of three answers: someone looked at it, someone marked it, or someone tested it. Only one of those three is actually capable of seeing what matters. The human eye can only ever catch visible soil. It has no way to see pathogen load, because pathogen load isn’t visible. Whatever a person can see with their own eyes was never going to be the whole picture, and the research bears that out again and again.
A surgeon gets applause. An EVS tech gets a pay stub. One of them prevents more infections than the other, and it’s not who you think.
Environmental Services staff earn a national median of $39,310 a year, well below the $100,210 median for registered nurses in the same hospitals (U.S. Bureau of Labor Statistics, 2025). They are among the lowest paid people in the building, and easy to overlook, and they sit directly on the front line of infection prevention. Not adjacent to it. Not supporting it from a distance. On it. Every surface a patient touches, every high-risk room turned over between cases, every terminal clean that stands between one patient and the next one, runs through their hands first.
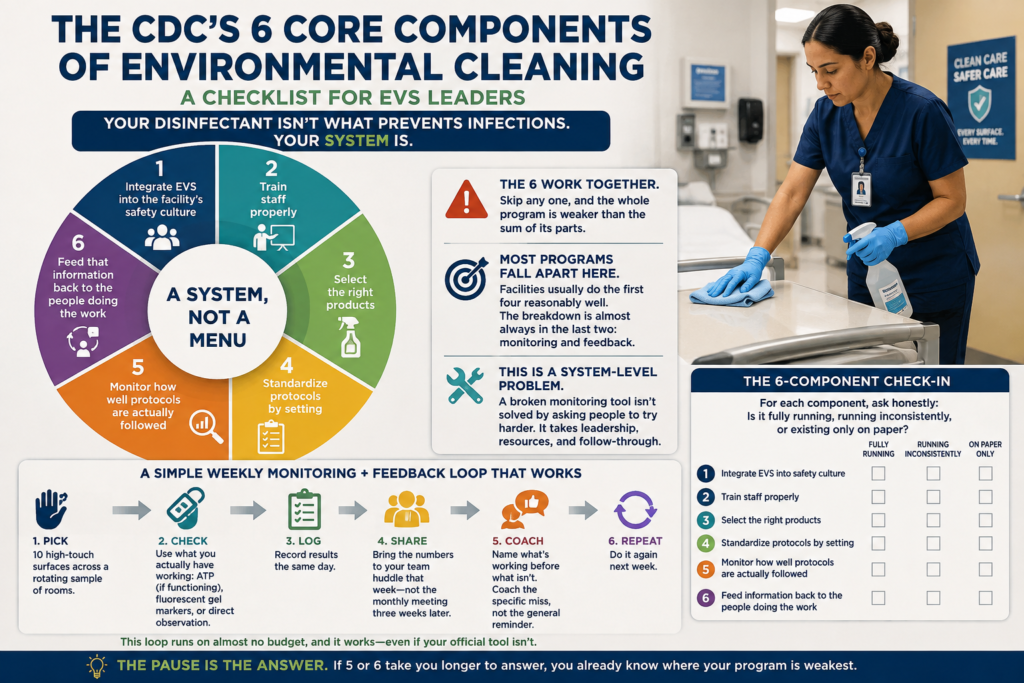
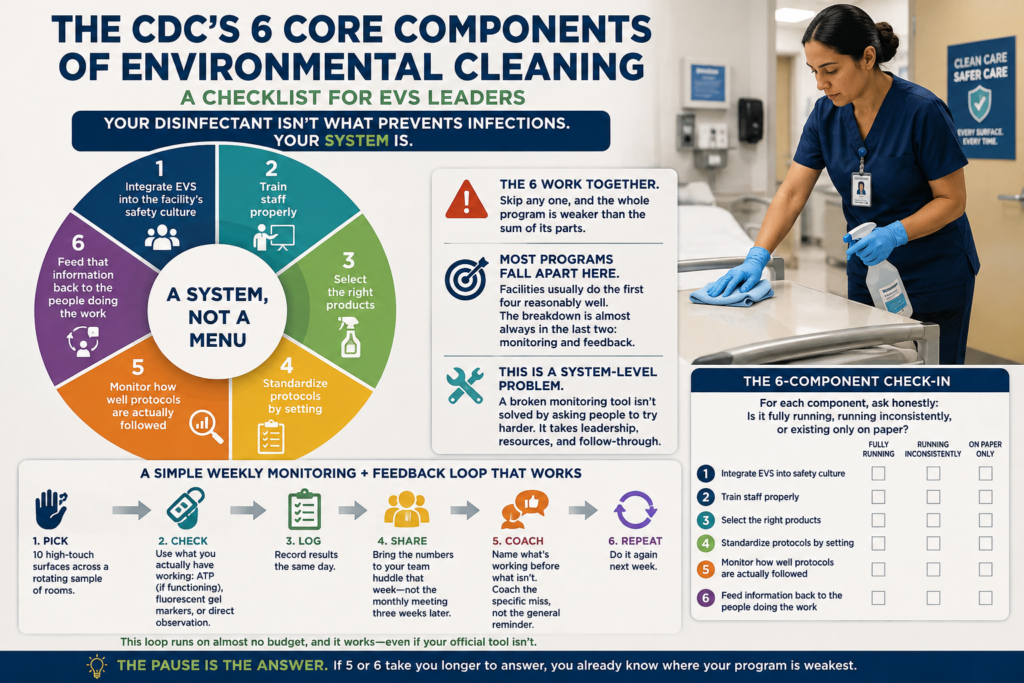
The Centers for Disease Control and Prevention, the CDC, lays out six core components for an environmental cleaning program:
Integrate Environmental Services, EVS, into the facility’s safety culture
Train staff properly
Select the right products
Standardize protocols by setting
Monitor how well those protocols are actually followed
Feed that information back to the people doing the work
CDC is explicit about one thing that gets lost in the summary version: these six work as a system, not a menu. You don’t get to run four of them well and skip the other two. Skip any one, and the whole program is weaker than the sum of its parts.
For years, infection prevention conversations treated Environmental Services as a support function. A separate department. A cost center. The people who clean after everyone else goes home. That era is ending. The 2026 guidance is explicit: if your EVS team is not staffed, trained, and monitored, that is a leadership failure, not a staff failure.
The guidance documents do not use the word blame. They use the word accountability. The expectation has moved from “did the room look clean” to “can you prove it is clean, and can you show who is responsible when it is not.”
My thoughts on promoting from within. #EnvironmentalServices #Leadership #Mentoring #Recognition #Joy
Why Low Budget Doesn’t Mean Low Standard You don’t need a multi-million dollar capital equipment budget to lower your Hospital-Acquired…